Quality management for dental clinics works best when quality is built into each step where the work happens, not checked only at the end. The goal isn't to eliminate every mistake. It's to make errors visible early, fixable by the people closest to the process and useful for the team's learning.
A clinic discovers that a patient record is incomplete when it's time to bill. It realizes an approved treatment plan never got a next step when the patient has already lost interest. It notices the schedule wasn't updated when two people argue about which provider should see a patient. The problem seems to be at the end of the workflow, but it almost always started earlier, at the moment a piece of information, a responsibility or a handoff was left undefined.
That's why quality management shouldn't start with the final inspection. Inspection is necessary in critical processes, but a mature operation tries to build quality in where the work is done.
My position is simple: when a clinic depends on the owner to find and fix every inconsistency, it doesn't have quality control. It has a central rescue service. That eats up leadership time, slows decisions and teaches the team to push problems on to the next step.
Late inspection or quality at the source
The ISO organizes quality management into seven principles, including customer focus, leadership, engagement of people, a process approach, improvement and evidence-based decision making. For a dental clinic, the practical point is important: quality doesn't belong to a single department, and it isn't just about checking documents. It comes from combining a clear process, a team able to act and reliable data to learn from results.
Two management models help show the difference.
| Model | How it works | Likely effect on the clinic |
|---|---|---|
| Late inspection | The mistake travels through the workflow and someone checks it at the end of the day, week or month | More fixing, delays, lost context and dependence on the owner |
| Quality at the source | Each handoff has a minimum condition to move forward, someone responsible for checking it and a planned response for exceptions | Problems show up earlier, fixes cost less and learning happens close to the cause |
Quality at the source doesn't mean the front desk, the dentist or billing has to solve everything alone. It means each area needs to know three things: what can't move forward incomplete, what it's allowed to fix and when to escalate.
This design avoids two common extremes. In the first, nobody stops the flow for fear of slowing things down. In the second, every small exception goes up to the owner. Good management creates autonomy within clear limits.
Following one problem from start to finish
Consider a hypothetical case. A treatment plan was approved, but the first appointment was never scheduled. Two weeks later, management finds it on the open items list and asks the treatment coordinator to follow up. The easy reaction is to ask for more follow-up calls. The more useful analysis is to rebuild the handoff.
Did the patient leave the case presentation with a clear decision? Was the payment arrangement recorded consistently? Was there a matching opening on the schedule? Was someone responsible for the next contact? Did the next step have a date? Was the reason it wasn't scheduled recorded?
A single open item can have several causes. Harvard Business Review warns against automatically looking for a single cause in problems that tend to have many. For a clinic, the consequence is practical: don't treat every stalled treatment plan as a front desk failure or a lack of patient interest. Separate objections, capacity, communication, payment terms, missing ownership and record quality before you act.
The owner stops asking "who forgot?" and starts asking "at which point did the workflow lose what it needed to move forward?" That shift reduces snap judgments and improves the quality of the fix.
Five quality checkpoints that protect growth
1. First contact and scheduling: don't let demand come in without context
The first quality checkpoint isn't filling in every field. It's capturing the information needed for the next decision. Lead source, reason for the visit, provider or specialty, preferred contact channel and next step can be more useful than a long patient record that nobody keeps up to date. Make the fields you truly need required.
Owner's decision: define which fields are essential to book an appointment, which can be completed later and who corrects conflicting information.
Process metric: percentage of new contacts that reach the schedule or the CRM with a defined next step and owner.
Risk revealed: the clinic may blame marketing for low conversion when, in reality, demand is being lost in the handoff between first contact and the visit.
2. Front desk and check-in: don't let handoffs depend on memory
When a patient arrives, the quality checkpoint is keeping the status and any open items that affect the visit consistently up to date. Important information shouldn't exist only in a conversation, on a sheet of paper or in the memory of whoever checked the patient in.
AHRQ's 2024 report on patient safety culture in medical offices gathered survey results from 1,164 outpatient offices of different types. Patient care tracking and follow-up, along with teamwork, were among the areas with the highest composite scores. The data isn't specific to dentistry, but it supports a transferable idea: continuity and coordination are observable dimensions of quality, not abstract qualities of the team.
Owner's decision: choose which status changes need to be visible to both the front desk and the clinical team, and when an open item blocks the workflow versus simply flagging it.
Process metric: percentage of visits with the status updated at the agreed time.
Balancing measure: perceived wait time and extra workload for the front desk. A control that lengthens the line without improving continuity needs to be redesigned.
3. Clinical records: protect continuity without reducing quality to filling in fields
Patient records and clinical documentation follow their own technical and professional responsibilities. Business management shouldn't define clinical content for operational convenience. Its role is to create the conditions for records to be completed at the right time, by an authorized person, with access and retrieval that fit the routine.
Owner's decision: clearly separate clinical records, operational notes and internal communication, avoiding parallel fields with confusing purposes.
Process metric: percentage of visits whose expected documentation was completed within the time frame set by the clinic and any applicable requirements.
Risk revealed: when the team uses loose notes to make up for a poorly defined process, the clinic may have information but not reliable continuity.
4. Treatment plans and follow-up: require a deliberate next step
A treatment plan shouldn't leave a conversation labeled only as "thinking it over." That status needs to mean something. There may be an objection to address, a timeline the patient asked for, the need for an additional evaluation or a scheduling limitation. Without a reason and a next step, the pipeline fills up with cases that look like opportunities but don't guide any work.
Owner's decision: define the minimum conditions for each follow-up stage, including an owner, a review date and a criterion for closing the case.
Process metric: percentage of pending treatment plans with a valid reason and next step.
Result metric: time between acceptance and the planned start of treatment, read alongside clinical need, the patient's choice and schedule capacity.
5. Billing: fix the event before it contaminates the report
The month-end close isn't the best time to find out that payments, expenses or payment terms were recorded inconsistently. Checking needs to happen close to the event, while receipts, people and context are still available.
In 2025, the WHO released a guide on measuring quality in health services that recommends aligning indicators with the improvement goal, covering outcomes, processes, essential inputs and possible unintended consequences. The same guidance highlights an important cycle: poor-quality data leads to less trust and use, and low use reduces the pressure to improve the data itself. For a clinic, that explains why abandoned reports rarely improve on their own. You have to fix the routine that produces the information.
Owner's decision: determine which financial events need same-day checking, which discrepancies can wait and who has the authority to correct them.
Process metric: percentage of financial events checked within the agreed time frame.
Result metric: number and value of corrections needed after the close.
The quality card for one handoff
The clinic doesn't need a long manual to get started. It can build a quality card for one critical handoff, with four questions:
- What has to be correct for the case to move forward?
- Who checks it, and what can that person fix without extra approval?
- Which signal makes the mistake visible in the same shift or the same day?
- Which measure will show whether the change improved the workflow without hurting another part of the operation?
Hypothetical example: an accepted treatment plan moving to the first appointment.
| Element | Working definition |
|---|---|
| Condition to move forward | Patient's decision recorded, consistent payment terms and next step defined |
| Owner | The person who closes the conversation or receives the confirmation, per internal rules |
| Immediate signal | Acceptance with no appointment, task or documented reason |
| Process measure | Percentage of acceptances with a next step before the end of the day |
| Result measure | Time until the planned first appointment |
| Balancing measure | Schedule overload, front desk rework and patient understanding |
This card has to fit into the routine. If it takes a long meeting for every case, it was poorly designed. If it doesn't distinguish a normal situation from an exception, the same is true.
Test small before turning it into a rule
The Institute for Healthcare Improvement (IHI) proposes three questions to guide improvement: what are we trying to accomplish, how will we know a change is an improvement and what change can we make that will result in improvement. Then the PDSA cycle lets you plan, do, study and act on a small-scale test before rolling it out broadly.
In a dental clinic, that might mean following the next ten accepted treatment plans instead of redesigning the entire follow-up process at once. Before the test, the team writes down a prediction. For example, it expects the main failure to be the lack of an owner. Afterward, it compares the hypothesis with what actually happened.
The IHI recommends reflecting on what was expected, what was observed, any unintended effects and the next test. It also acknowledges that changes that don't lead to improvement should be stopped or revised. That's freeing: the owner doesn't have to defend a rule just because it was their idea. They need to learn fast enough to fix the design.
Training should show up in behavior, not on an attendance sheet
When a mistake reveals a knowledge gap, the instinct is to schedule a training session. Sometimes that's the right answer. Other times, the problem is an unclear rule, a poorly configured screen, missing access, conflicting priorities or no time to do the task.
A McKinsey analysis published in 2026 notes that one-off training sessions and detailed manuals don't guarantee that skills carry over into daily work. The most consistent transformations combine shared metrics, structured playbooks, coaching and local adaptation, so that data guides priorities and people turn information into action. Although the examples come from manufacturing, the principle applies to practices: capability is proven when the team makes better decisions in a real case.
Before asking for new training, investigate four possibilities:
- The person doesn't know what to do.
- The person knows, but the rule conflicts with another priority.
- The person knows, but doesn't have the access, time or information.
- The person does it, but the measurement system doesn't capture the result.
Each diagnosis calls for a different response. Training closes a knowledge gap. Process redesign resolves a conflict. Configuration and permissions remove an operational barrier. Reviewing the metric fixes invisibility. Treating everything as a training problem is expensive and unfair.
Where HartSystem, ProDent and Pro365 AI fit in
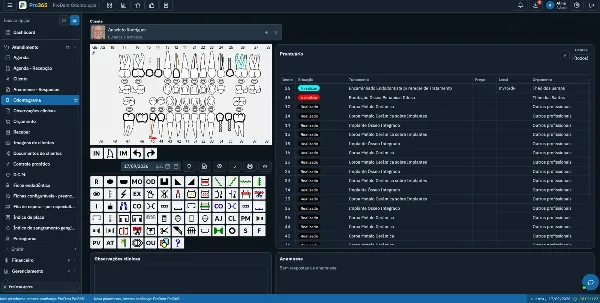
ProDent combines scheduling, financial management, digital patient records, CRM, management indicators, Pro365 AI, hands-on support and personalized consulting in one integrated platform. That integration matters because quality problems cross departments: an incomplete patient record can affect communication, scheduling, history, billing and later analysis.
Technology doesn't choose the clinic's quality standard on its own, doesn't replace clinical judgment and doesn't automatically fix incomplete records. HartSystem can help turn information into routine, but the owner is still responsible for setting priorities, roles, escalation criteria and reviews.
The most productive combination is this: use the system to make the event visible, Pro365 AI to shorten questions about how to use the software and read the data, the indicators to track behavior and results, and consulting to challenge the interpretation and make the change stick in the real routine.
Start with the mistake that costs the most by the time you find it
Don't try to launch a quality program for the whole clinic next Monday. Choose one handoff where mistakes show up late and cost a lot. It could be a new contact with no next step, a visit with no status update, an accepted treatment plan that never gets scheduled or a payment that needs fixing at month-end.
Look at ten cases, define the minimum condition to move forward, give the people closest to the event the authority to fix it and track one process measure, one result measure and one balancing measure. Then review what the team learned.
The sign of maturity isn't a clinic with no mistakes. It's a clinic that finds them early, fixes them close to the source and turns what happened into a better process. Sustainable growth depends less on big speeches about excellence and more on this quiet discipline, repeated every day.
With Pro365 GO, the new ProDent that runs 100% on the web, scheduling, records, treatment plans and billing share the same data, so gaps in a handoff are easier to spot. Book a demo to see it with your clinic's workflow.